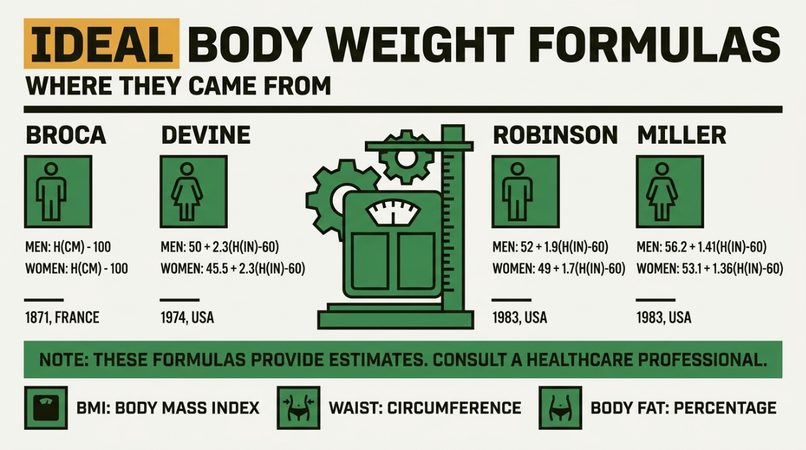
Short answer: the Devine, Hamwi, Robinson and Miller formulas were never designed to tell you what to weigh. They were built for clinical purposes, principally medication dosing, where a standardised reference weight is more useful than actual bodyweight. They disagree with each other by up to nine kilograms at taller heights, which is a fair measure of how precisely any of them describes an individual.
Where each one came from
- Hamwi, 1964. Developed in the context of diabetes management, as a quick bedside method for estimating a reference weight.
- Devine, 1974. Published in a paper on gentamicin dosing. It has become the most widely used clinically, largely by convention rather than demonstrated superiority.
- Robinson, 1983. An attempt to fit better data, published in the American Journal of Hospital Pharmacy alongside Miller in the same year.
- Miller, 1983. Same context, different coefficients, producing a flatter curve that rises less steeply with height.
Notice what none of these is: a study of what weight makes people healthiest. Pai and Paloucek traced the origins of these equations and found that Devine in particular was proposed without a supporting derivation, and it persisted because it was convenient.
How far apart they land
| Height (men) | Devine | Hamwi | Robinson | Miller | Spread |
|---|---|---|---|---|---|
| 165 cm | 61.2 kg | 62.1 kg | 61.4 kg | 63.2 kg | 2.0 kg |
| 175 cm | 70.3 kg | 72.8 kg | 69.0 kg | 68.8 kg | 4.0 kg |
| 185 cm | 79.4 kg | 83.4 kg | 76.5 kg | 74.3 kg | 9.1 kg |
At average height they broadly agree. At 185 cm they disagree by more than nine kilograms, because the coefficients per inch differ substantially and the error compounds with height. Any single figure quoted from one of these formulas carries that uncertainty invisibly.
What they are legitimately used for
| Application | Why not actual bodyweight |
|---|---|
| Aminoglycoside and other drug dosing | Some drugs distribute in lean tissue, so dosing on total mass overshoots |
| Ventilator tidal volume | Lung volume tracks height, not weight, and over-inflation causes injury |
| Renal function estimation | Standardises comparison across body sizes |
| Clinical nutrition support | Estimating requirements where actual weight is distorted by oedema or obesity |
In these settings the formulas are doing real work, and the imprecision matters less because they are applied alongside clinical judgement and monitoring.
Why they mislead as a personal goal
- Only two inputs. Height and sex. Nothing about frame, muscle, or composition.
- No account of muscle. A trained person will sit above every figure while being in excellent health.
- Historical populations. Derived from limited samples decades ago, not representative of the current general population.
- A single number implies precision that four disagreeing formulas plainly do not have.
Better measures for a personal target
- Waist to height ratio under 0.5. Captures fat distribution, which these formulas ignore entirely. Calculate it.
- Body fat percentage. Separates lean mass from fat, the actual difference between two people of the same height. Tape method.
- Healthy BMI range, which is wider and more honest than a single figure, though it shares the muscle blind spot. Range for your height.
- Performance and how you feel at a given weight, which no equation supplies.
If you still want a number
Use the healthy BMI range rather than a formula, and treat it as a band rather than a target. At 175 cm that is roughly 57 to 76 kg, a nineteen kilogram span, and that width is honest rather than unhelpful. Where you sit inside it depends on muscle mass, frame and what you are training for.
FAQ
What is the Devine formula?
Men: 50 kg plus 2.3 kg per inch over 5 feet. Women: 45.5 kg plus 2.3 kg per inch. Published in 1974 in the context of gentamicin dosing.
What is the Robinson formula?
Men: 52 kg plus 1.9 kg per inch over 5 feet. Women: 49 kg plus 1.7 kg per inch. Published in 1983.
Which ideal body weight formula should I use?
For clinical dosing, whichever your institution specifies, usually Devine. As a personal goal, none of them. Use body fat percentage and waist to height ratio instead.
Why is my ideal weight lower than my actual weight?
Often because you carry more muscle than the formula assumes. Check body fat percentage before concluding you need to lose weight.
Sources
- Devine BJ. Gentamicin therapy. Drug Intelligence and Clinical Pharmacy, 1974.
- Hamwi GJ. Therapy: changing dietary concepts. In: Diabetes Mellitus: Diagnosis and Treatment. American Diabetes Association, 1964.
- Robinson JD, Lupkiewicz SM, Palenik L et al. Determination of ideal body weight for drug dosage calculations. American Journal of Hospital Pharmacy, 1983.
- Miller DR, Carlson JD, Loyd BJ, Day BJ. Determination of ideal body weight for drug dosage calculations. American Journal of Hospital Pharmacy, 1983.
- Pai MP, Paloucek FP. The origin of the ideal body weight equations. Annals of Pharmacotherapy, 2000.
- World Health Organization. Body mass index classification. who.int
General information, not medical advice. Clinical dosing decisions belong with qualified prescribers.
GramGoal Team. We build nutrition calculators and price-check the supplement market monthly. General information, not medical advice. See our methodology and affiliate disclosure.